

Every heart has a story.
Real patients. Real journeys. Real Heart Success Stories.
The video library.
Real patients and their journeys, in their own words and in the national press.




One patient story
From planning my funeral to planning vacations.
One patient came to me after a lifetime of sitting with the dying, only to find himself making the same plans for his own failing heart. After the medications had done all they could, an implanted therapy reset the signals a struggling heart sends the brain, and gave him his life back.
A heart success story. Shared with permission, told without names.
The words that stay with you.
He did not just treat my heart. He gave my kids their father back.
He said the word amyloidosis out loud when four other doctors had missed it.
Your story could be the reason someone else calls in time.
If treatment gave you your life back, telling that story might hand someone else the courage to ask for help. It stays yours: named or anonymous, you decide.

Your plan lives in one of these.
Read the heart honestly, name what is really happening, and put a real plan in front of you.
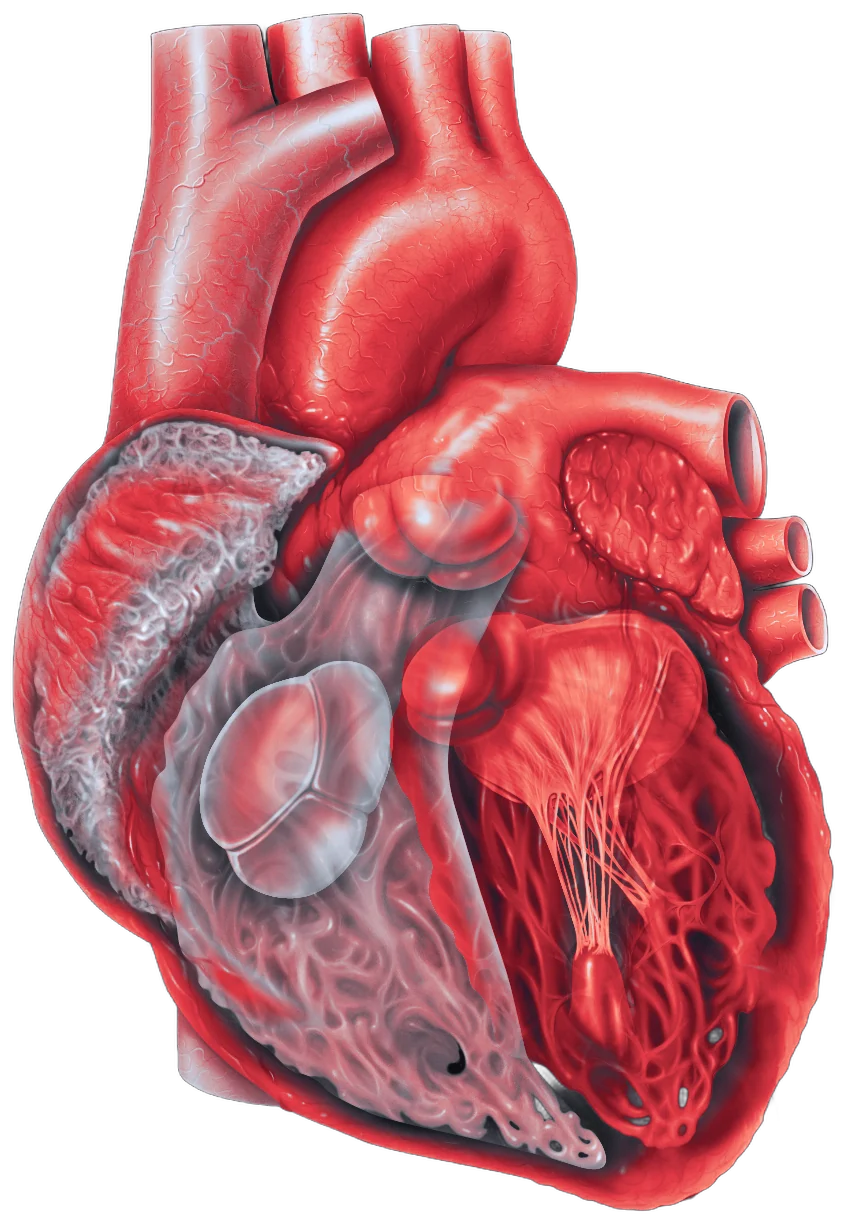
Advanced Heart Failure
The sickest hearts, managed to the last tolerated milligram.
Guideline-directed therapy at real doses, not starter doses, watched closely and adjusted early. The goal is written in your terms: fewer hospital stays, more life between visits.
Heart Transplantation
Candidacy, the gift itself, and the years of keeping it.
Candidacy, listing, the wait, the surgery, and the decades after. As Director of Heart Transplantation Services I stay responsible for the whole arc, including the parts nobody sees.
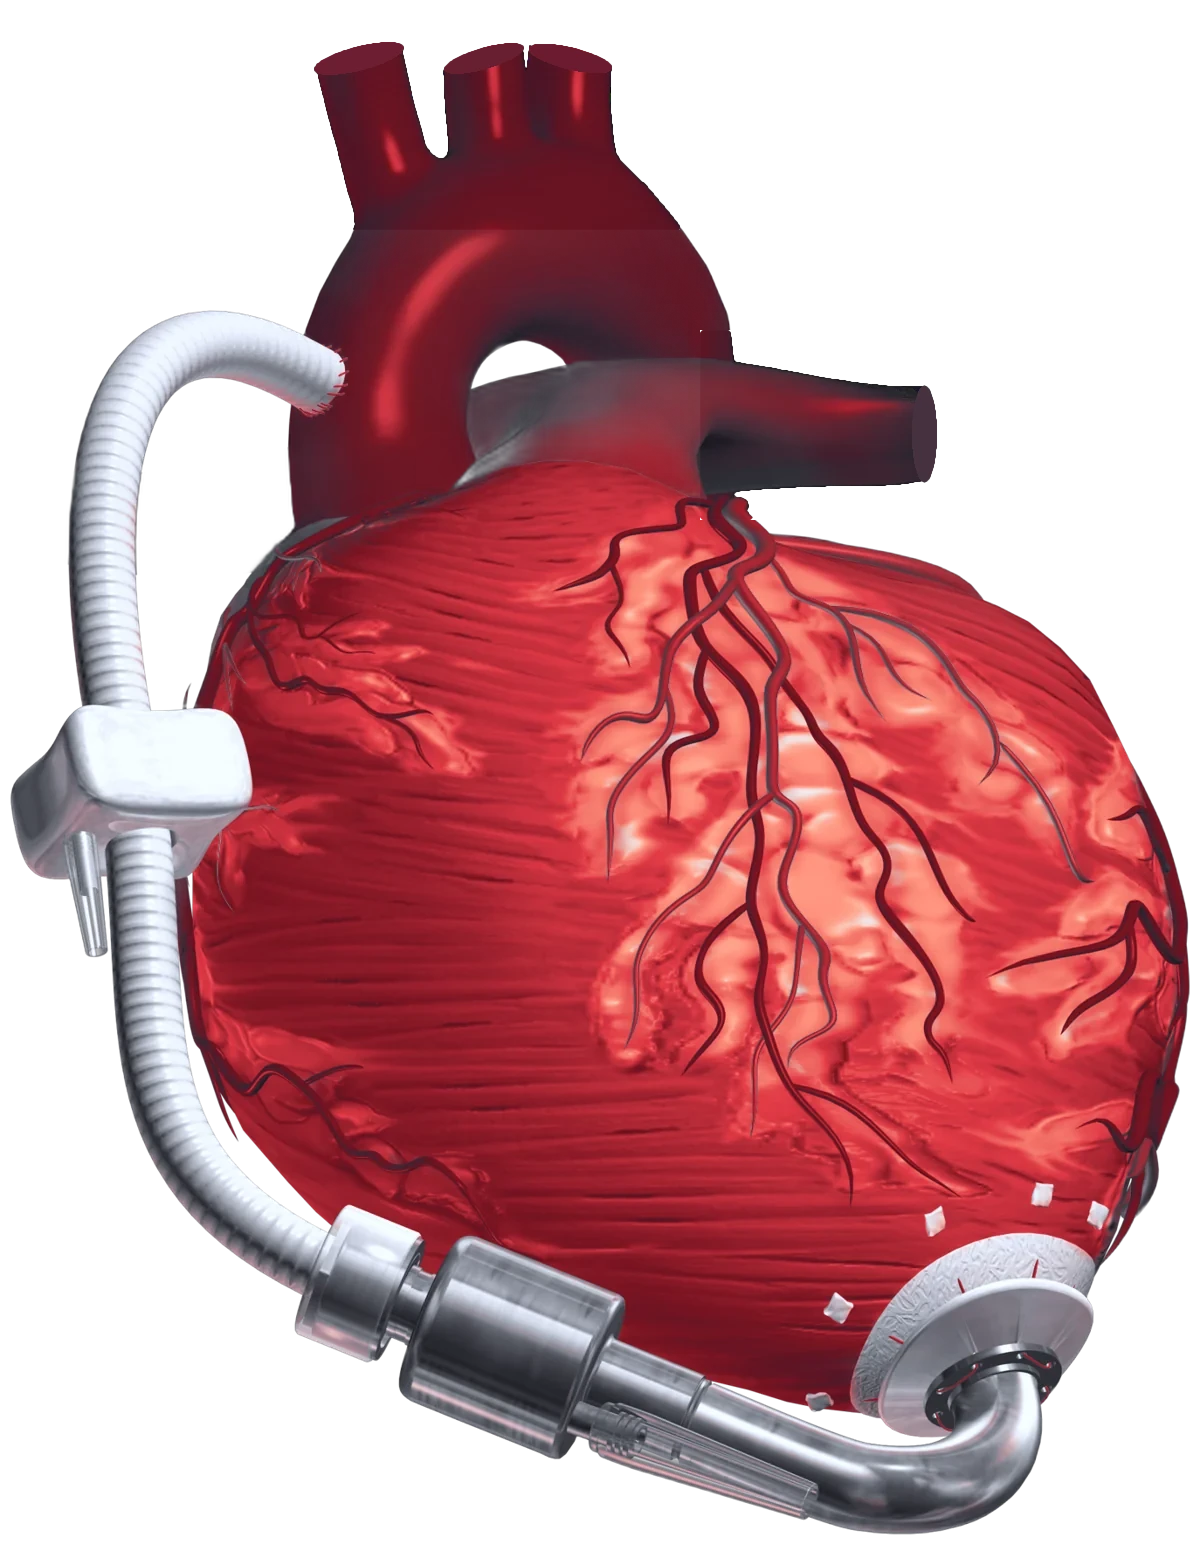
Mechanical Circulatory Support
Machines that buy time when the heart cannot keep up alone.
LVAD, ECMO, Impella, IABP. For some a bridge to transplant, for others a destination, and for a few, the pause that lets their own heart recover.
Cardiac Amyloidosis
A disease that hides in plain sight, caught earlier on purpose.
A stiff, thickening heart that gets called normal aging. A dedicated program exists to name it earlier, because named early, it is treatable.
Pulmonary Hypertension
The pressure the right heart carries until someone measures it.
Pressure on the right side of the heart, usually found late. We measure early on purpose, then treat with targeted therapy before the pressure wins.
Cardiogenic Shock
When the heart fails suddenly and minutes are the whole game.
When the heart fails suddenly, the protocol has to be faster than the panic. A standing shock team keeps blood moving while the heart decides whether it can come back.

A weakening pump, not a stopped one. It is a diagnosis to manage, not a death sentence.
Breathlessness on stairs, swollen ankles, sleeping propped up. Caught early, these are a clinic visit instead of an ICU stay.
A pump that does the heart's work, and a system that decides who gets a donor heart and when. Both are more livable than the fear suggests.
We once confirmed it only at autopsy. Now it is treatable, if someone thinks to look.
A program is a promise a region can keep.
A hospital can buy the machine. The promise is the team around it: the protocols, the training, the referral lines that hold at 3 a.m. That is what I build.
Where you live should not decide whether you reach world class cardiovascular care. The Heart Success network reaches referral hospitals and underserved communities across the Mid-South.
Many heart failure patients are in rural areas.
Heart failure mortality per 100,000, 1999 to 2020
Hover, tap, or use the arrow keys to compare a single year.
Rural patients have higher rates of mortality, likely due to lack of access to care.
When patients have access to advanced therapy centers, they end up with lower mortality rates.
Age adjusted heart failure mortality, rural versus urban, per 100,000, 1999 to 2020. Sources: Bozkurt B, et al. J Card Fail. 2024. Lu DY, et al. Circ Heart Fail. 2024.
500 plus
mechanical circulatory support cases placed, and still counting.

One throughline: keep the person,
not just the pulse.
Across all six domains the question is the same. Not just whether the heart can keep beating, but whether the person can keep living a life they recognize. Every plan I write is measured against that. Honest reads, named diagnoses, and choices a patient and their family can actually carry.
Keep the person, and the pulse tends to follow.